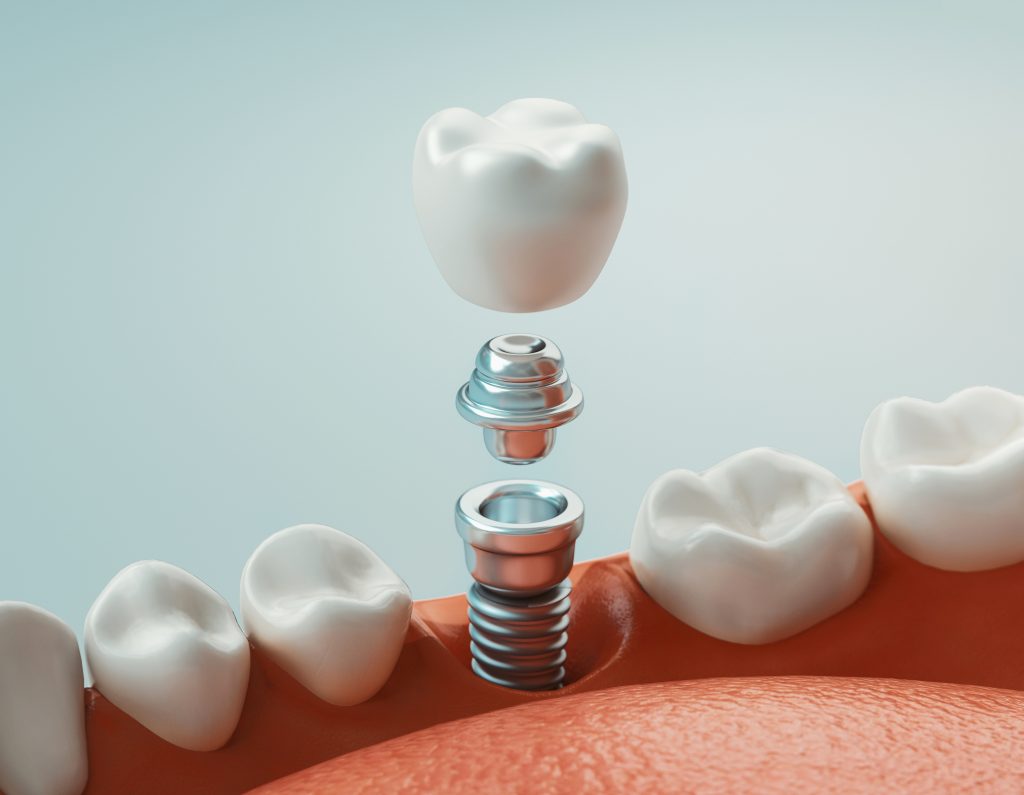
Why Dental Implants Are a Long-Term Solution for Missing Teeth
Dental implants serve as a permanent tooth replacement solution because they undergo osseointegration, a biological process where biocompatible titanium posts fuse directly with the jawbone to replicate natural tooth roots. Unlike traditional bridges or removable dentures that rest on the gums or rely on neighboring teeth, implants transfer chewing forces directly into the bone to prevent resorption and preserve facial architecture. When surgically placed by an oral and maxillofacial surgeon and maintained with routine oral hygiene, dental implants can maintain optimal bite function, structural stability, and aesthetics for a lifetime.
Why Are Dental Implants Considered a Permanent Tooth Replacement Solution?
Tooth loss triggers progressive structural and biomechanical changes within the oral cavity. When a natural tooth is extracted or lost due to trauma or advanced periodontal disease, the alveolar bone that once supported the root ceases to receive mechanical stimulation from daily mastication. According to Wolff’s Law of bone remodeling, skeletal tissue adapts to the physical loads placed upon it. In the absence of functional stimulation, osteoclasts break down the unneeded bone matrix, leading to rapid alveolar bone resorption in both height and width during the first twelve months following extraction.
Conventional tooth replacement modalities, such as removable partial dentures, complete dentures, and tooth-supported fixed dental prostheses (bridges), address visible aesthetic deficits but fail to halt subgingival bone loss. Removable prosthetics rest entirely on the soft mucosal tissue, applying external compressive pressure that can accelerate bone atrophy. Fixed bridges span edentulous gaps by anchoring onto adjacent teeth, requiring the irreversible reduction of healthy enamel while leaving the underlying edentulous ridge unstimulated.
Modern dental implants solve this biological challenge by functioning as endosteal root substitutes. Once surgically placed into the maxilla or mandible, the implant body establishes a direct structural connection with vital bone. This interface allows physiological occlusal loads to be transmitted deep into the skeletal architecture, stimulating continuous osteoblastic activity and bone remodeling. By preventing localized atrophy, implant restorations preserve facial dimensions, maintain the natural gingival contours, and keep adjacent teeth from tipping or supra-erupting. For individuals evaluating long-term restorative care, consulting specialized resources on implant dentistry treatments provides valuable insight into contemporary clinical options.
How Does the Biological Process of Osseointegration Work?
The long-term clinical durability of implant therapy relies fundamentally on osseointegration. First defined by Professor Per-Ingvar Brånemark, osseointegration represents the direct structural and functional connection between living bone tissue and the surface of a load-bearing alloplastic fixture, without the interposition of non-calcified connective or fibrous tissue.
The Four Phases of Cellular Osseointegration
Following the surgical preparation of an osteotomy, the host tissue engages in a precise, highly coordinated biological healing sequence:
- Hemostasis and Fibrin Scaffold Formation (Minutes to Hours): Immediately upon fixture placement, blood fills the microscopic void between the implant and surrounding bone walls. Platelets aggregate to form a stable fibrin clot, releasing vital cytokines and growth factors, including Platelet-Derived Growth Factor (PDGF) and Transforming Growth Factor-Beta (TGF-β).
- Angiogenesis and Mesenchymal Cell Recruitment (Days 1 to 7): Neovascularization occurs as newly formed capillary sprouts penetrate the fibrin network. This microvascular bed delivers oxygen and nutrients while recruiting undifferentiated mesenchymal stem cells and osteoprogenitors directly to the implant surface.
- Osteogenesis and Woven Bone Deposition (Weeks 1 to 4): Recruited osteoblasts synthesize an unmineralized collagenous matrix (osteoid) on the oxidized titanium surface. This osteoid rapidly mineralizes into immature woven bone, establishing initial secondary biological stability through primary contact osteogenesis.
- Lamellar Remodeling and Interfacial Maturation (Months 1 to 6+): Under the influence of progressive physiological loading, immature woven bone undergoes rigorous remodeling. Osteoclasts resorb unorganized trabeculae while osteoblasts lay down dense, highly organized parallel lamellar bone, creating a resilient biomechanical anchor capable of bearing full masticatory forces.
Once osseointegration is complete, the implant fixture does not possess a periodontal ligament; it is directly fused to the skeletal matrix. Because healthy bone tissue continuously remodels in response to balanced occlusal stresses, a fully integrated implant remains anchored for decades, provided the surrounding peri-implant tissues remain free of pathogenic bacterial biofilms.
What Engineering and Materials Drive Dental Implant Durability?
The exceptional structural resilience of modern dental implants is the product of advanced biomaterial engineering and metallurgical science. Implants are predominantly fabricated from commercially pure titanium (Grade 4) or medical-grade titanium alloys, most notably Ti-6Al-4V (titanium-aluminum-vanadium), which offer superior tensile strength, low modulus of elasticity, and remarkable corrosion resistance within the biological environment.
Passivation and Surface Microtopography
Titanium exhibits superior biocompatibility due to its instantaneous chemical passivation. When exposed to oxygen during manufacturing, titanium forms a microscopic, chemically stable titanium dioxide (TiO2) layer measuring 2 to 10 nanometers in thickness. This ceramic-like dielectric layer prevents the release of metallic ions into surrounding tissues and provides an ideal substrate for osteoblast adherence and matrix deposition.
Modern implant surfaces are treated with advanced subtractive and additive engineering techniques, including sandblasting with large-grit particles and acid-etching (SLA), anodization, or hydrophilic chemical modifications. These micro- and nano-textured topographies exponentially increase the effective bone-to-implant contact (BIC) area, accelerating cellular attachment and significantly reducing the healing timeline required prior to functional loading.
Prosthetic Component Materials
The transmucosal and coronal portions of the restoration utilize advanced dental ceramics, including monolithic zirconia (yttria-stabilized tetragonal zirconia polycrystal) and lithium disilicate. These biomedical-grade materials replicate the optical translucency and compressive strength of natural dental enamel while offering superior resistance to fracture, wear, and chemical degradation from oral acids. Because titanium and ceramic components are inorganic, they are chemically impervious to bacterial demineralization and dental caries.
How Do Single Implants Compare to Full-Arch Restorations?
Implant reconstruction is customized to treat the exact degree of edentulism, ranging from single-tooth deficits to total dental arch clearance. The core biomechanical requirements remain consistent, but the surgical and restorative execution adapts to structural demands.
Single-Tooth and Segmental Restorations
When an isolated tooth is missing, an individual titanium implant is positioned precisely within the edentulous space to support a custom abutment and single ceramic crown. This modality preserves the integrity of adjacent natural teeth by eliminating the need to prep neighboring abutments for a conventional three-unit bridge. For quadrant tooth loss, multiple adjacent missing teeth can be restored using an implant-supported fixed partial denture, wherein two or more fixtures support a connected multi-unit ceramic bridge, reducing the total number of implants required while maintaining occlusal stability.
Full-Arch Reconstruction Protocols
In cases of terminal dentition, severe periodontitis, or complete edentulism, a full set of dental implants provides a rigid, fixed alternative to unstable removable prosthetics. Full-arch rehabilitation strategies strategically place four, five, or six implants throughout the maxilla or mandible to support a full-arch monolithic zirconia or titanium-reinforced bridge.
Unlike traditional complete dentures, which lose retention as the underlying alveolar ridge progressively resorbs, a full-arch dental implant bridge anchors directly into dense cortical bone. This eliminates mucosal irritation, slipping, and the need for messy denture adhesives while restoring up to 90% or more of natural masticatory efficiency. Patients can eat a comprehensive, fibrous diet and speak without concern over prosthetic destabilization.
How Does Bone Volume Affect Long-Term Implant Success?
Sufficient alveolar bone height, width, and density represent the foundational prerequisites for long-term osseointegration. Following tooth extraction, the surrounding alveolar socket undergoes horizontal bone loss of approximately 30% to 50% within the first six months, followed by gradual vertical reduction. When teeth have been missing for years, or when localized pathology such as periapical cysts or advanced periodontitis has destroyed bone, the residual ridge may lack the dimensions required to anchor an endosteal implant with primary stability.
A minimum of 1.5 to 2.0 millimeters of healthy cortical bone is generally required around the circumferential periphery of an implant fixture to ensure adequate vascular supply and withstand occlusal forces. When pre-operative cone-beam computed tomography (CBCT) imaging demonstrates insufficient skeletal volume, specialized oral and maxillofacial reconstructive surgical techniques are utilized to reestablish an ideal foundation.
What Bone Grafting Techniques Support Implant Stability?
Reconstructive bone augmentation reestablishes alveolar ridge anatomy prior to or simultaneously with fixture placement. Understanding bone grafting essentials allows patients to comprehend how surgeons re-create lost skeletal architecture using osteoconductive, osteoinductive, and osteogenic biomaterials.
Ridge Preservation and Guided Bone Regeneration
Socket preservation grafting (ridge preservation) is performed immediately following tooth extraction by packing bone allograft or xenograft into the empty socket and sealing it with a collagen barrier to prevent ridge collapse. In sites with established horizontal or vertical bone defects, surgeons utilize Guided Bone Regeneration (GBR). GBR involves placing particulate bone graft material against the deficient skeletal boundary and covering it with a resorbable or non-resorbable barrier membrane. This membrane prevents fast-proliferating soft tissue fibroblasts from invading the graft site, allowing slower-growing osteogenic cells to regenerate dense bone.
Sinus Lift Augmentation
In the posterior maxilla, tooth loss is compounded by pneumatization—a natural biological process where the maxillary sinus cavity expands downward into the alveolar ridge. A sinus lift (sinus floor elevation) is performed to gently elevate the Schneiderian membrane lining the sinus cavity and place bone graft material beneath it. This creates ample vertical bone height to securely anchor implants in the upper premolar and molar regions. Patients seeking deeper information can review advanced bone grafting procedures to understand how modern surgical biologics accelerate osteogenesis.
When Are Graftless Dental Implant Techniques Appropriate?
For patients presenting with extreme maxillary or mandibular ridge atrophy who wish to avoid extensive multi-stage bone grafting procedures or prolonged healing timelines, advanced graftless protocols offer a reliable restorative pathway. Utilizing graftless dental implants allows oral and maxillofacial surgeons to leverage existing, dense basal skeletal structures rather than rebuilding deteriorated alveolar ridges.
These techniques include strategically angling posterior implants at 30- to 45-degree inclinations (such as in the All-on-4 configuration) to maximize contact with dense anterior cortical bone and bypass the maxillary sinus or inferior alveolar nerve canal. In cases of profound maxillary resorption, extra-maxillary fixtures—such as zygomatic implants anchored into the strong zygomatic arch (cheekbone) or pterygoid implants anchored into the sphenoid bone—provide immediate mechanical stability. This approach facilitates immediate full-arch functional loading, enabling patients to receive a fixed temporary prosthetic on the day of surgery.
When Is Corrective Jaw Surgery Necessary Prior to Implant Placement?
In complex restorative cases, missing teeth are often accompanied by severe skeletal malocclusions, developmental jaw discrepancies (such as severe Class II or Class III relationships), or significant craniofacial asymmetry. Placing implants into misaligned skeletal bases can result in poor biomechanical loading vectors, non-aesthetic prosthetic emergence profiles, and premature implant failure caused by excessive non-axial shear forces.
When severe skeletal disharmony compromises restorative feasibility, oral surgeons perform corrective jaw surgery (orthognathic surgery) in coordination with dental rehabilitation. By surgically repositioning the maxilla (via Le Fort osteotomies), the mandible (via bilateral sagittal split osteotomies), or both, surgeons establish ideal skeletal bases and correct inter-arch relationships. Once the structural jaw alignment is stabilized, subsequent dental implant placement can be executed with optimized axial loading angles, ensuring the structural stability and facial harmony of the final prosthetic restoration.
How Can Patients Prevent Peri-Implant Disease and Ensure Long-Term Health?
Although dental implants cannot develop conventional dental caries, their long-term clinical survival depends upon the health of the surrounding peri-implant mucosa and underlying crestal bone. The primary biological threat to osseointegration is peri-implant disease, an inflammatory condition triggered by the accumulation of pathogenic oral biofilm. Peri-implant disease progresses through two distinct clinical phases:
| Condition | Clinical Characteristics | Reversibility | Bone Loss Present |
|---|---|---|---|
| Peri-Implant Mucositis | Erythema, edema, soft tissue inflammation, bleeding on gentle probing. | Completely reversible with improved plaque control and debridement. | No radiographic bone loss. |
| Peri-Implantitis | Deeper probing depths, mucosal suppuration, progressive crestal bone resorption, mobility in terminal stages. | Irreversible bone loss; requires surgical intervention and antimicrobial therapy to arrest progression. | Yes, progressive circumferential bone loss. |
Maintaining a disease-free peri-implant environment requires a structured, lifelong maintenance protocol. Patients must perform daily mechanical plaque removal using soft-bristled manual or sonic toothbrushes, non-abrasive toothpastes, interdental brushes with coated plastic wires, and oral irrigators (water flossers). Regular professional periodontal assessments, occlusal evaluations, and gentle debridement with implant-safe titanium, carbon-fiber, or ultrasonic scaler tips are essential every three to six months to intercept early inflammation before irreversible crestal bone loss can occur.
Frequently Asked Questions
How long do dental implants typically last?
With precise surgical placement into adequate bone and consistent daily oral hygiene, dental implants can last a lifetime. While the titanium fixture is designed to remain permanently integrated with the jawbone, the overlying ceramic crown, bridge, or abutment may experience routine mechanical wear and require replacement or tightening after 15 to 20 years.
Can dental implants develop cavities or tooth decay?
No, dental implants cannot develop cavities. The implant fixture is made of medical-grade titanium and the restorative crown is composed of high-strength ceramic or zirconia, neither of which is susceptible to bacterial acid demineralization. However, the surrounding mucosal tissue and jawbone remain vulnerable to bacterial plaque, which can cause peri-implantitis if oral hygiene is neglected.
What is the difference between traditional implants and graftless options?
Traditional dental implants are inserted vertically into the alveolar ridge and often require pre-implant bone grafting if severe bone resorption has occurred. Graftless dental implants utilize specialized surgical techniques—such as tilting posterior implants or anchoring into denser zygomatic or pterygoid bone—to achieve robust primary stability without requiring extensive preliminary bone augmentation.
Is bone grafting always necessary before receiving dental implants?
No, bone grafting is only required when a patient lacks sufficient alveolar bone height, width, or density to structurally support the implant fixture. Individuals with adequate native bone volume and healthy ridge dimensions can proceed directly with implant placement without additional bone augmentation procedures.
How do implant-supported prosthetics compare to traditional removable dentures?
Implant-supported restorations are rigidly anchored into the skeletal jawbone, eliminating the slipping, speech difficulties, and soft tissue irritation associated with removable dentures. In addition, implants stimulate the surrounding bone to halt jaw resorption and restore up to 90% of natural chewing force, whereas conventional dentures can accelerate bone loss due to persistent surface friction against the gums.